
Unlearn in Amyotrophic Lateral Sclerosis
Since 2020, more than 5,000 people have enrolled in Phase 2 and 3 ALS trials without a broadly approved treatment to show for it — and every one of those studies holds evidence for the next one. Unlearn turns that evidence into a compounding advantage so each trial informs the next, decisions come earlier, and new therapies can ultimately reach patients faster.
Digital twins power that advantage. Generated from baseline data, each one forecasts how a participant would be expected to progress under placebo or standard of care. In design, those forecasts show how a candidate population and endpoint behave before the protocol locks. In a randomized trial, pre-specified in the analysis plan with the control arm intact, they sharpen the comparison so a real effect is detected with fewer participants or more certainty. When randomization is not an option, as in many small open-label ALS studies, they give a single-arm study a more robust external control. After readout, they separate expected progression from treatment effect in the data you already have.
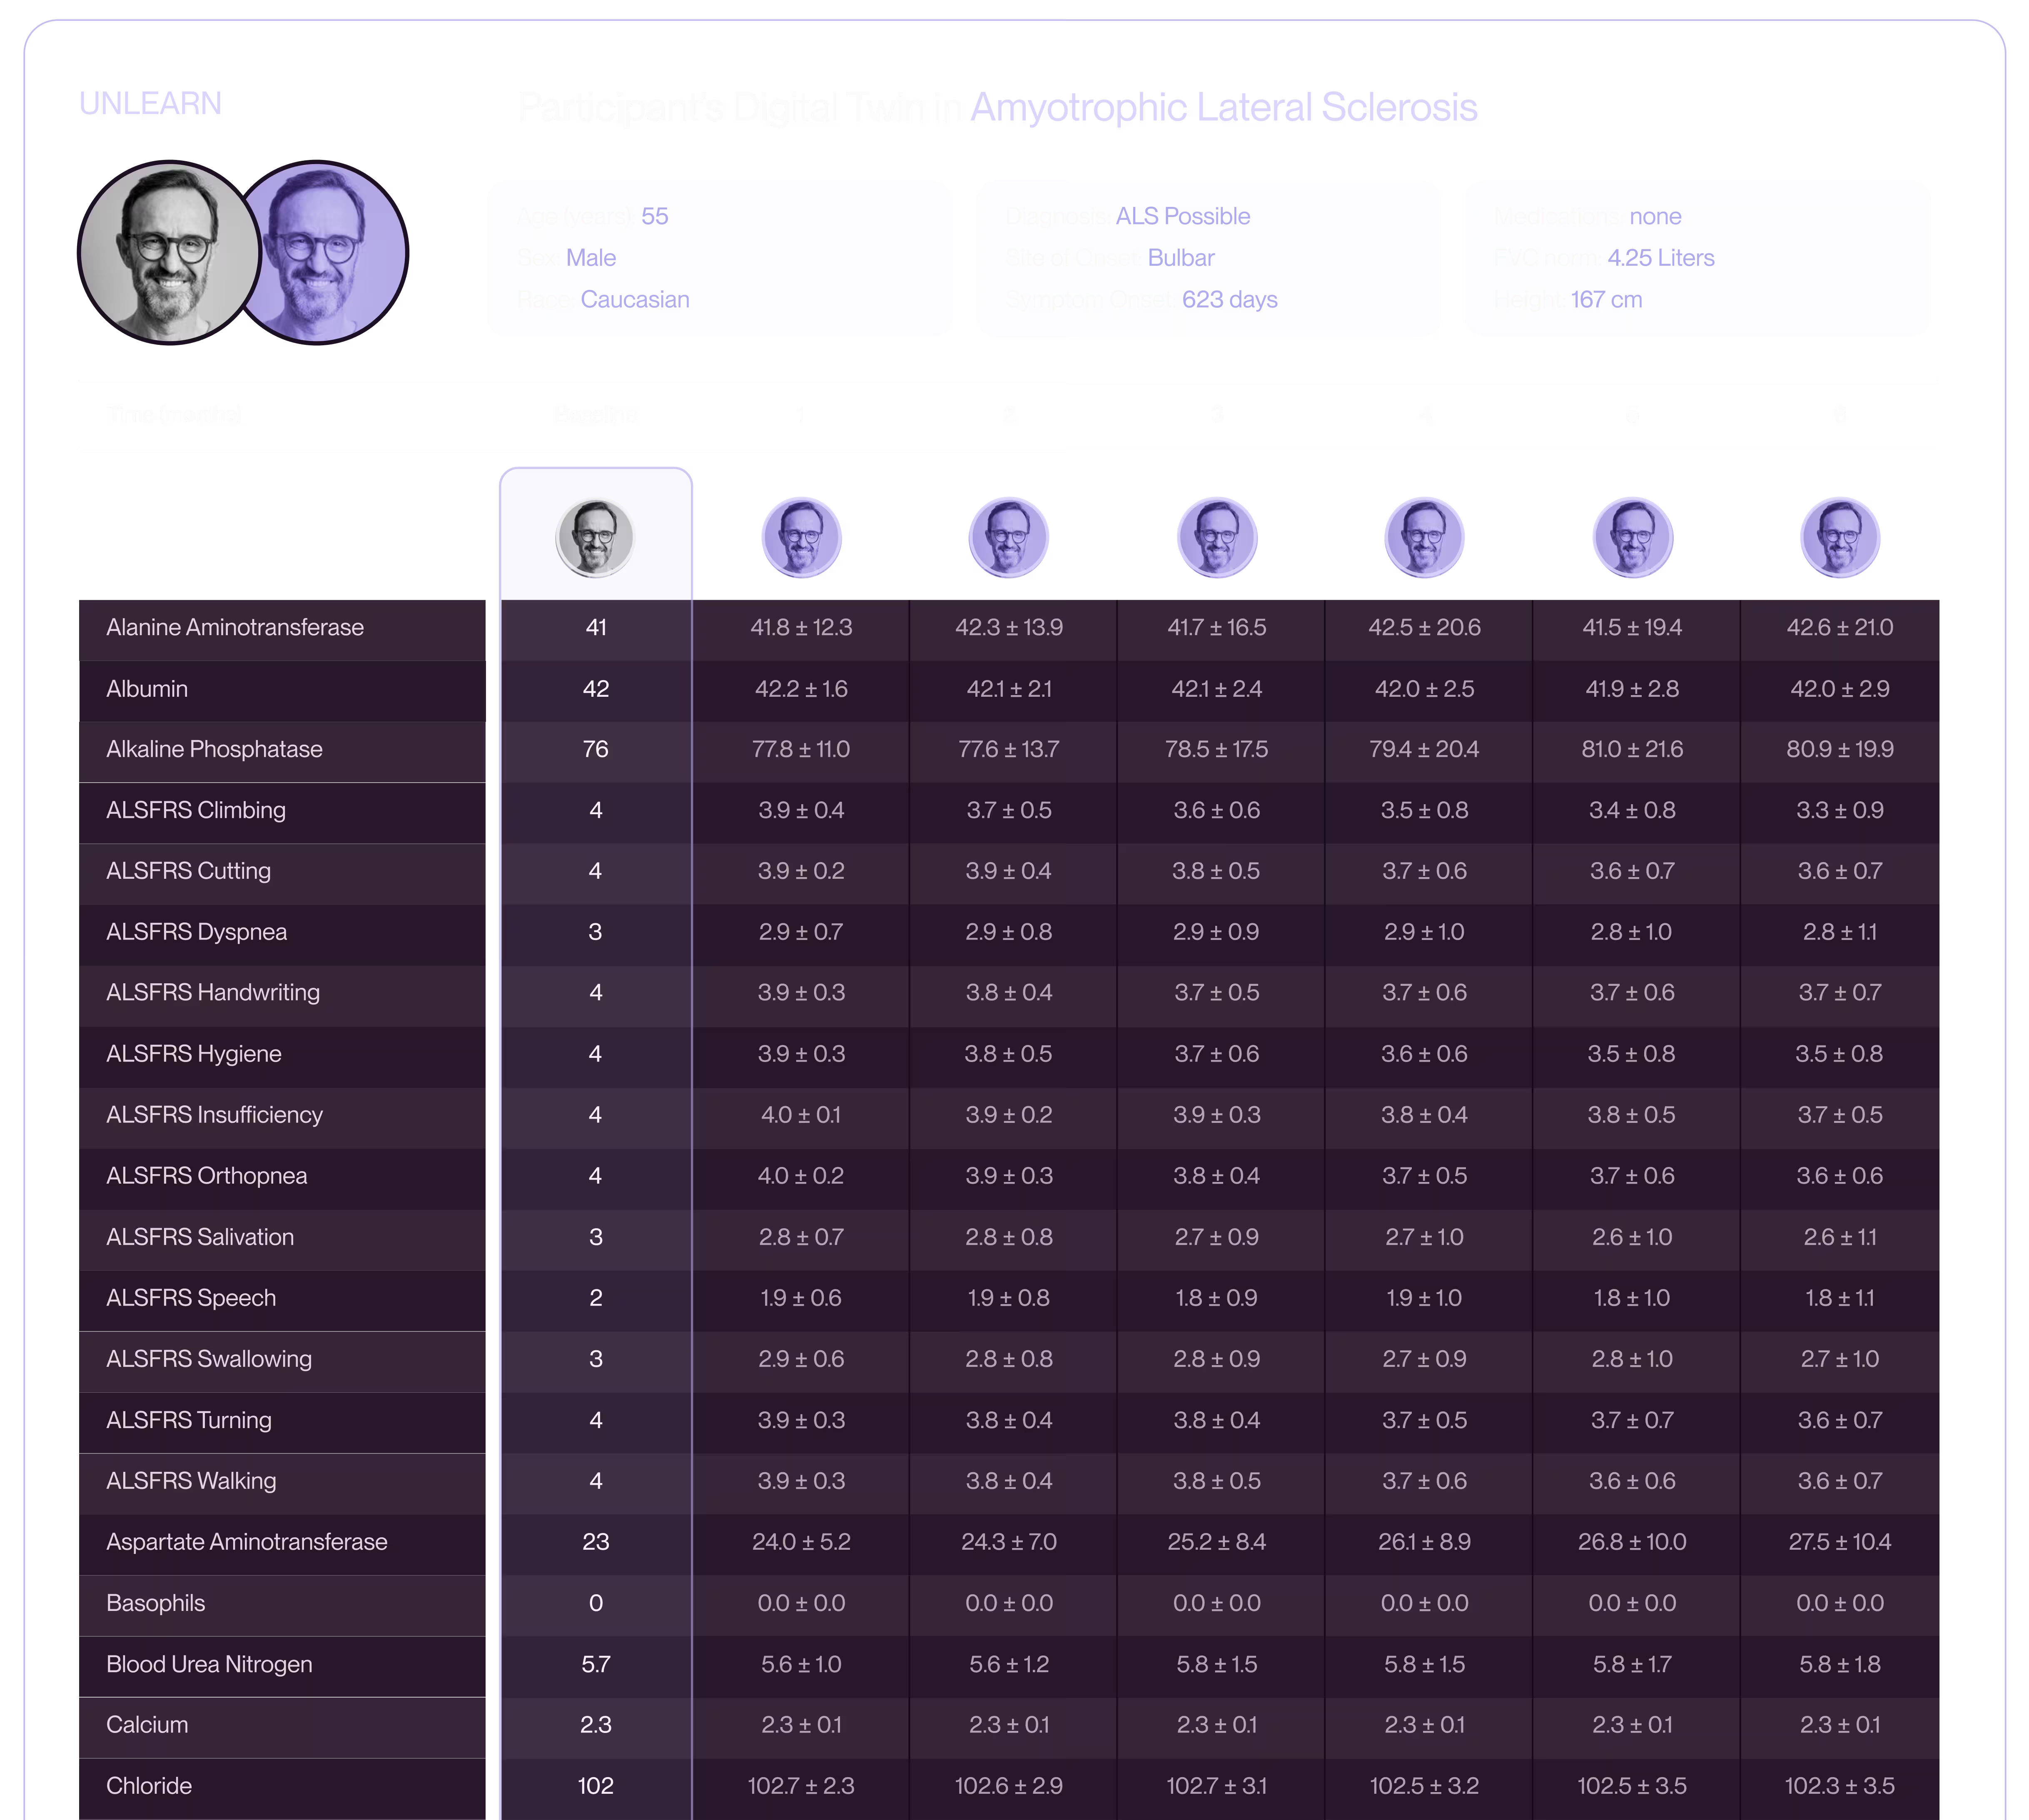
Unlearn's Digital Twin Generator for ALS is trained on data from more than 13,600 people with ALS, spanning all stages of disease severity, to generate comprehensive, longitudinal disease forecasts for each enrolled trial participant.


Key Numbers
Impact in ALS
Turn a completed study into a smaller next trial
Once a study has read out, the next question is what the next trial should look like. In a re-analysis of a completed Phase 3 ALS trial of ceftriaxone (513 participants), incorporating participants' digital twins reduced treatment-effect variance by 18% on ALSFRS-R at 48 weeks — enough to maintain statistical power with 92 fewer participants, and with analyses projecting roughly $14M in enrollment savings at Phase 3 scale.
About this study
We re-analyzed a completed Phase 3 trial of 513 participants randomized to ceftriaxone in a 2:1 ratio, with the ALS Functional Rating Scale–Revised (ALSFRS-R) at 48 weeks as the primary outcome. Using our EMA-qualified PROCOVA method, we generated digital twins of study participants and applied linear regression. These analyses used a pre-specified ALS DTG. Prognostic scores derived from participants' digital twins reduced treatment-effect variance for the clinical outcomes without compromising Type-1 error control.
Sample-size reductions at 48 weeks reached 20% across ALSFRS-R total, respiratory, and bulbar scores and forced vital capacity (16% at 24 weeks). The projected enrollment savings reflect Phase 3 enrollment costs falling from about $77M to $63M with 92 fewer participants.
Lock a smaller sample into the design
Sample size, endpoints, and eligibility are still in play before the protocol locks. A leading global pharma sponsor sized its ALS Phase 1b/2a study to detect slowing in plasma neurofilament light (NfL); scenario simulations showed the same signal with a 20% smaller sample, and the sponsor locked that reduction into its final design. Combining digital twins with Bayesian methods charts a path to a 28% reduction in future programs — roughly $250K per patient in program savings.
About this engagement
We built an ALS-specific digital twin generator, ran scenario simulations on the sponsor's actual inclusion and exclusion criteria and proposed design parameters, and layered PROCOVA-family covariate adjustment on top — leveraging regulatory frameworks already applicable to the indication.
“Working with Unlearn to mine their extensive, well-curated database through the use of the ALS DTG will enable us to explore smarter designs and make confident and informed decisions as we plan our Phase 1/2 trial. Ultimately, these insights can help us to move faster for people living with ALS who are waiting for new treatment options.”
Eric Green, M.D., Ph.D., Co-founder and CEO, Trace Neuroscience
Read the press release ↗Give every open-label participant a built-in control
When early ALS studies are small and open-label, the readout is hard to read on its own. In ProJenX's PRO-101 study of prosetin, digital twins serve as the external control in the 12-month open-label extension — per-participant treatment effects, with no changes to trial conduct. In an open-label case study presented with ProJenX, re-analyzing 35 treated participants against their digital twins raised power to detect a 20% slowing of plasma NfL from 72% to 82%.
About this study
ProJenX is applying Unlearn's ALS Digital Twin Generator in PRO-101, a hybrid Phase 1 study of prosetin, a CNS-penetrant MAP4K inhibitor. Digital twins serve as a simulated placebo arm in the open-label extension, offering a patient-specific baseline for comparison without a traditional control group. Beyond comparison, digital twins support endpoint selection, refinement of inclusion and exclusion criteria, and flagging participants likely showing a treatment effect.
“Digital twins help us make the most of the data we're getting from here. In this open-label study, digital twins obviously provide us with built-in placebo controls for each participant...they have a lot of key advantages over propensity score matching or other natural history controls that allow us to have more confidence in the data we're taking out of that person-intraperson comparison.”
Erin Fleming, COO, ProJenX · ALS Drug Development Summit 2025, Boston, MA
Solutions
Every clinical trial is a chain of high-stakes decisions.
Unlearn can help at any point in your study. Digital twins, data, and AI strengthen each one, so study teams can commit with confidence, and evidence compounds from one decision to the next.
Sample size, eligibility criteria, endpoints, and comparators are still up for discussion, and governance approval is ultimately the gate before the study design can move forward. Unlearn simulates the study against your actual criteria, validates against precedent, and quantifies the design trade-offs, so your team walks into governance with data-driven numbers that support key study design decisions.
In ALS, that means testing your eligibility criteria against harmonized historical data, comparing designs across the endpoints you are considering, and pressure-testing the progression assumption behind the sample size, all before anything is locked in the protocol.
Build and compare trial-design scenarios to evaluate endpoints, eligibility criteria, sample size, and constraints, and to pressure-test sample size and PTS assumptions.
Add digital twins of participants to the statistical analysis plan (using PROCOVA, our EMA-qualified, FDA-supported method) to reduce sample sizes in randomized controlled trials while maintaining power, or boost power without adding new patients.
Design robust, efficient externally controlled and hybrid studies, whether randomization is not an option or a smaller control arm is the goal: anticipate the impact of the external comparator and select the eligibility criteria that give an open-label or single-arm study its best chance of a clear, interpretable readout. Digital twins can serve as individualized comparators on their own, be combined with a propensity model for added robustness, or strengthen a traditional historical control rather than replace it.
The protocol is locked. The analysis plan can still be optimized.
Every interim decision, whether to stop for efficacy, stop for futility, re-estimate the sample size, or revisit key design assumptions, rests on an interim estimate. Pre-specified digital twin analyses, added to the statistical analysis plan before unblinding, tighten that estimate without adding patients, and design scenarios can be re-run when new evidence emerges mid-study.
Add digital twins of participants to the statistical analysis plan (using PROCOVA, our EMA-qualified, FDA-supported method) before unblinding to raise power at interim looks and in subgroup analyses.
Re-run design scenarios against new evidence, whether a competitor readout, a new publication, or blinded data drifting from design assumptions, to confirm the current design holds or identify what to change.
Unlearn scientists generate digital twins from baseline data already collected, draft the pre-specified analysis for the SAP, and deliver the twin-adjusted analysis at interim and at readout.
The study has read out. The evidence is not finished.
Your completed study holds more evidence than the readout showed. Re-evaluating the data with regulatory-aligned methods separates expected disease progression from treatment effect, for a sharper estimate of the effect across primary and secondary endpoints.
Re-analyze the completed study against each participant's digital twin to separate expected disease progression from treatment effect, whether the study met its endpoint or missed it.
Read the result against evidence that did not exist when the trial was designed, including other studies that have since read out.
Carry what the study revealed into the next design: a validated view of disease progression, a better estimate of the effect, and a design that starts from what you now know.
Technology
Digital Twin Generators
Digital Twin Generators (DTGs) are machine learning models that produce individualized forecasts, called digital twins, of each trial participant's expected clinical outcomes under placebo or standard of care. These forecasts are generated using baseline data and include predicted values for item-level assessments, labs, vitals, and other clinical measures. DTGs are powered by a machine learning architecture that Unlearn developed, optimized for probabilistically modeling complex, multivariate, clinical time-series data.
ALS-DTG-4.1 is trained on de-identified, participant-level data from more than 13,600 people with ALS, drawn from randomized controlled trial control groups and observational studies spanning all stages of disease severity. Sources include the Pooled Resource Open-Access ALS Clinical Trials (PRO-ACT) Database, the NEALS Biorepository, the Pooled Resource Open-Access Clinical Research (PRO-ACE) Database, and APST Research, and the model is regularly updated with new endpoints and new data.
Regulatory Acceptance
Paving the regulatory path for AI in clinical trials
Unlearn's methods have been recognized and supported by both U.S. and European regulators. The European Medicines Agency officially qualified our digital twins-based method for use in Phase 2 and 3 trials with continuous outcomes. The U.S. FDA provided positive feedback, supporting its use in covariate-adjusted analyses across clinical development.
CHMP qualifies PROCOVA and that the proposed procedures could enable increases in power and/or decreases in sample size in phase 2 and 3 in clinical trials with continuous outcomes.
FDA recommends that sponsors adjust for covariates that are anticipated to be most strongly associated with the outcome of interest… the sample size and power calculations can be based on adjusted or unadjusted methods.
Evidence
Driving impact across clinical development
Explore how our partners are accelerating their clinical development programs with us.


